AI Agent Platforms for EHR and Payer Portal Workflow Automation
Agents automate healthcare workflows by navigating EHR and payer portals without API setup.
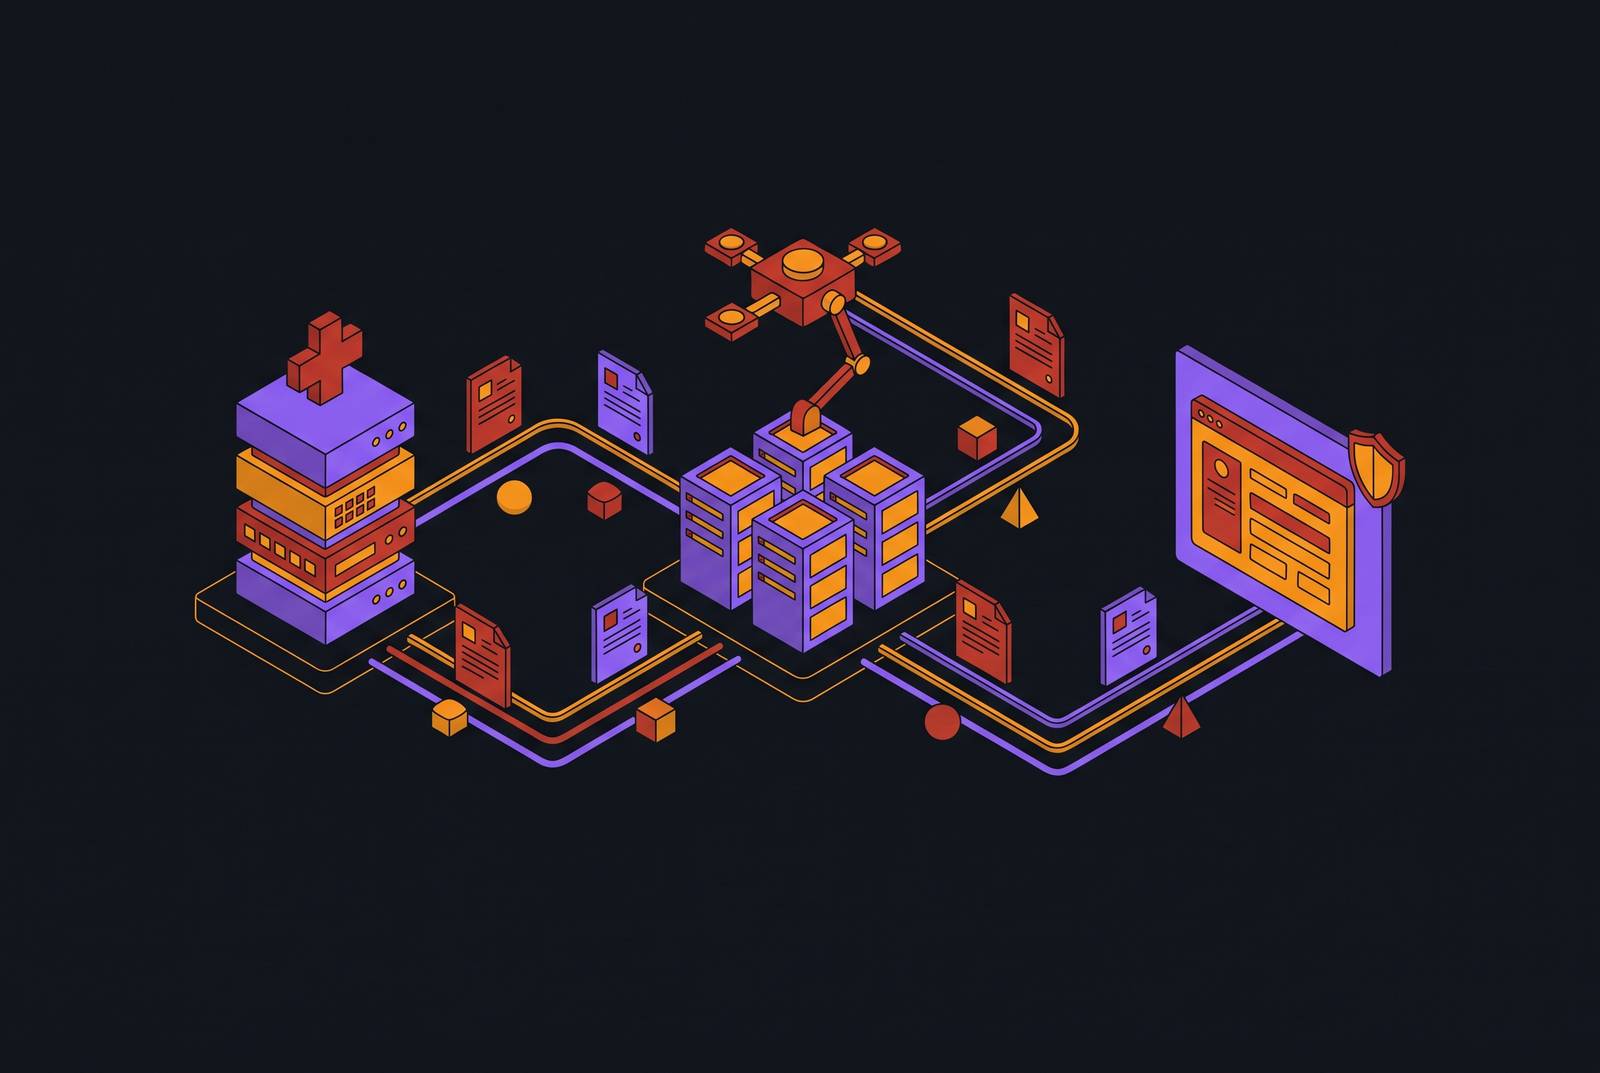
Computer-using AI agents automate healthcare administrative workflows without API integrations by reading screens, clicking, typing, and navigating EHRs and payer portals as staff would. Their architectural advantage is continuity across systems, from eligibility checks and prior authorization to structured EHR write-back. Choosing a platform means checking how it handles a whole workflow, including the tasks and conversations within it.
Why EHR and payer portal workflows resist automation through conventional means
Healthcare administration crosses systems that were never designed to communicate with one another. The EHR has the patient record, while a payer portal has the submission requirements and authorization status. A response may then need to return to the EHR before the workflow is complete. Each boundary creates another handoff for the staff. Automating work inside one system does not resolve the transition to the next.
API integrations address these boundaries only where a formal connection exists. The long tail of payer portals, specialty workflows, and smaller practice configurations makes complete coverage difficult to achieve and maintain. A practice may have connectivity for one stage but none for the next. Where systems lack a connection, staff must read information in one interface and enter it in another.
Judgment between stages is harder to automate. Asteroid identifies this as a limitation of pre-LLM software, which could automate a stage in isolation but could not span the workflow chain with judgment. A payer response is not simply data to move. It can determine which action comes next and whether the available information is sufficient to proceed.
How do computer-use agents automate EHR and payer portal workflows without API setup?
Computer-use agents work through the interfaces staff already use. They read screens, click controls, type information, and navigate between systems rather than requiring a custom technical connection to each one. An unpublished API therefore does not itself prevent automation. Asteroid describes browser-agent fleets that read, classify, route, and fill forms across EHR and payer portals.
That differs from traditional scripted robotic process automation, or RPA. Fixed-coordinate scripts depend on a particular layout and can break when a portal changes. MFA, CAPTCHA, and ambiguous states also interrupt rigid scripts and create maintenance work. Computer-use architecture changes how an agent interprets the interface, but it does not justify unrestricted execution. Production-grade agents pause and route ambiguous states to a human reviewer.
APIs remain useful where they are available. They provide a formal technical connection, but each connection must be established and maintained, and many payer portals do not publish one. Computer-use agents remove API availability as a prerequisite for operating those portals. Asteroid also reports that in production deployments, a single non-technical operator shipped nine or more payer agents without help from engineers. This shifts configuration closer to the people who understand the workflow.
Voice AI serves a different, complementary role. It can navigate IVR trees, wait on hold, and speak with payer representatives, but voice alone does not operate portal screens or EHR interfaces. A workflow that includes both a payer call and an EHR update needs both capabilities. A platform can coordinate voice and computer-use agents so that the conversation and the screen-based action remain parts of one sequence.
The prior authorization workflow as the clearest case for end-to-end agent automation
Clinical information begins in the EHR, submission and status may sit in a payer portal, and a payer without a portal may require a fax-to-PDF layer. The result must then return to the EHR. Each stage depends on what happened before it. A submission tool alone leaves the surrounding retrieval, monitoring, and write-back work unresolved.
Computer-use agents can operate these interfaces without a custom integration at every boundary. Their scope includes moving from the source record to the submission channel and back to the record after a response. The connection is the operational gain. If an agent submits successfully but leaves staff to retrieve the decision and update the EHR, the practice still has a partially automated authorization workflow.
Billing an inactive plan or skipping required insurer approval can lead to a denial later, so submission must include checks of eligibility and authorization requirements. The workflow can flag missing or conflicting information before moving on, so staff can address it before it causes a preventable failure.
The CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) has operational provisions effective January 1, 2026, and FHIR API requirements effective January 1, 2027. The rule requires specific denial reasons and API-enabled authorization workflows. Where payer APIs exist or become available, an agent platform can use them together with portal navigation. The available channel changes without requiring the practice to redesign the underlying workflow.
How computer-use agents handle the rest of the revenue cycle: claims, denials, eligibility, and write-backs
Eligibility verification, claims submission, claims status, denial management, and EHR updates depend on information held in different systems. Asteroid identifies payer-facing back-end work as a particularly fragmented and lightly automated area. An automated eligibility check helps little if staff must move its result to the next stage by hand.
An agent checks coverage against live payer data, validates benefits, and flags coordination-of-benefits issues before the patient arrives. Errors caught at this stage can prevent downstream denials. Claims and denial workflows then extend the same screen-reading and form-filling approach into later payer interactions. These workflows help only if their results guide the next action without another staff handoff.
Referrals arrive by fax, EHR message, and unstructured PDF, requiring the agent to read the material, extract clinical and administrative information, and create a downstream record in the receiving system. Asteroid treats referral intake as a category of its own that relies heavily on fax. Reading the document is only the first step. The information must reach the system where subsequent work happens.
EHR write-back is the final and most fragile connection. The agent must resolve patient identity correctly and write structured data to the right record. A portal-only tool that cannot operate the EHR stops short of this requirement, as does a voice-only tool without a connected screen-based capability. Completion therefore depends on the destination record as much as the payer interaction.
Scheduling, cancellation recovery, and the front-end workflows computer-use agents also handle
Patient access uses the same architecture for a different bottleneck. Scheduling and cancellation recovery depend heavily on volume and speed. An agent reads provider availability in the EHR or practice management system, matches a patient or referral to an appropriate slot, and books it. The booking is a separate action from the conversation. Computer-use capability supplies the screen interaction needed to complete that action in the existing system.
An agent can reach waitlisted patients and book replacements when staff are unavailable, giving around-the-clock operation a direct role in filling last-minute openings. Voice can support the outreach, while computer use handles the schedule. Neither channel alone defines the complete workflow. The operational test is whether the accepted offer becomes a confirmed booking without another person navigating the calendar.
Scheduling a new patient from a referral requires work across systems. The agent receives the referral, reads the clinical information, identifies the appropriate provider and slot in the EHR, and books the appointment. Asteroid identifies scheduling and appointment management as an established, crowded category. The distinguishing capability is therefore not simply holding a scheduling conversation, but completing the chain from incoming information to recorded appointment.
What HIPAA compliance actually requires of any platform that touches PHI across these workflows
Screen-based access has the same HIPAA obligations as other forms of access. An agent operating on behalf of staff must remain within the access and safeguard requirements that govern the information it handles. Those obligations follow PHI through the workflow, including the systems and subprocessors involved. A platform’s ability to cross boundaries makes the controls at those boundaries more important.
For a practice evaluating that architecture, access scope is a practical starting point. Broad FHIR scopes that request more information than the task requires can violate the minimum necessary standard. Persistent conversation memory creates a different risk when it retains PHI between sessions in an ungoverned store. These stores often have not been audited. Showing that a workflow works does not prove that the way the deployment handles access and retention meets its obligations.
Contractual coverage must also follow the information. A vendor whose system creates, receives, or transmits PHI requires a signed Business Associate Agreement before PHI reaches it, and the obligation extends to relevant subprocessors, including the underlying LLM provider. The practice should establish which subprocessors touch PHI and whether each has the required agreement. The practice also needs a clear answer on retention, including the LLM data retention policy and whether zero-day retention is available. The platform should also be able to produce a full audit trail of agent actions across workflows and sessions.
Proposed requirements need to be distinguished from current obligations. The 2025 HIPAA Security Rule proposal would include AI systems that create, receive, maintain, or transmit ePHI in a written technology asset inventory. It would also remove the “addressable” designation for encryption and make it mandatory. SOC 2 Type II certification and HIPAA compliance are baseline evaluation criteria rather than workflow differentiators, and neither replaces scrutiny of how the platform handles PHI.
How to evaluate an AI agent platform for EHR and payer portal workflow automation
Platform evaluation should cover five dimensions, namely workflow coverage, system reach, compliance architecture, deployment timeline, and measurable performance. Workflow coverage starts with the complete sequence the practice needs to automate. Does the platform connect eligibility, prior authorization, claims submission, denial management, and structured EHR write-back, or stop after one stage? A handoff defines the remaining manual workload. The distinction is between a deliberate review of ambiguity and routine staff work needed to connect otherwise automated steps.
Can the platform operate payer portals without published APIs, as well as the EHR screens where staff complete their work? Payer breadth belongs within this test, including commercial, Medicare Advantage, Medicaid, and ACA Marketplace portals. Asteroid reports that its production deployments run across 40+ systems with 250+ agents. These figures give some context, but the practice needs coverage for its own payer mix, including portals it uses less often.
Compliance architecture should then be evaluated across that demonstrated scope. The questions are which subprocessors receive PHI, what agreements cover them, how long information persists, and whether actions can be audited. Deployment requirements deserve the same specificity. Months of integration work or a requirement to replace existing staff systems can erode the operational benefit. The suitable architecture learns the existing workflow rather than requiring the practice to rebuild it around the platform.
Useful benchmarks are claims statused per day, prior authorization turnaround time, denial rate before and after deployment, and provider schedule utilization. Aggregate percentages cannot substitute for these measures when they cannot be traced to a particular workflow at a particular practice. The platform should state what it will measure and how. The strongest evidence of end-to-end automation is a completed administrative sequence with measurable results, governed access, and human review reserved for the points that require judgment.